
GOT DIABETES? THE LATEST ON PERIPHERAL NEUROPATHY (TREATING PN WITH LOW LEVEL LASER THERAPY)
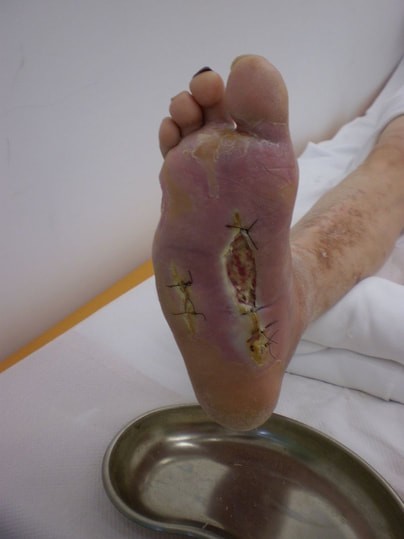
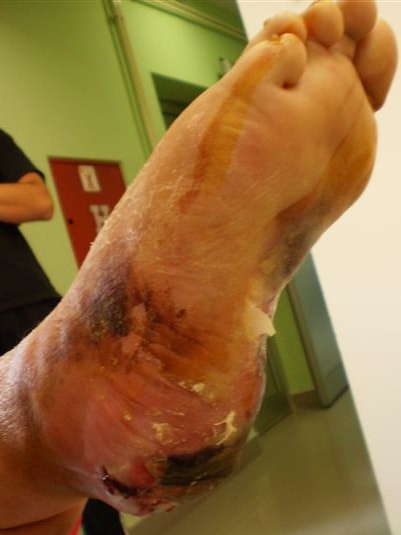
“Peripheral neuropathy refers to the conditions that result when nerves that carry messages to and from the brain and spinal cord from and to the rest of the body are damaged or diseased… Damage to these nerves interrupts communication between the brain and other parts of the body and can impair muscle movement, prevent normal sensation in the arms and legs, and cause pain.” From an article on WebMD called Understanding Peripheral Neuropathy: The Basics
With one in ten Americans having full-blown TYPE II DIABETES and over half of the rest of the adult population (mostly unaware of the fact) living with PRE-DIABETES — something most ‘Functional Medicine’ specialists say should actually be called ‘Diabetes’ — you can see how epic this problem really is. And despite pouring millions upon millions of dollars into WARNING THE POPULATION about this monster, all indications are that it’s getting worse instead of better (see link).
Furthermore, if you have Diabetes and are fortunate enough to avoid all of the other killers associated with it (CANCER, HEART DISEASE, STROKE, etc), it is not unlikely that you will die from complications of your amputation(s). One of the many miserable conditions directly related to Diabetes is Peripheral Neuropathy, otherwise known as PN.
I was getting ready to write an overview of PERIPHERAL NEUROPATHY, when I received an e-copy of the latest issue of PRACTICAL PAIN MANAGEMENT. The issue carried an article called Medical Management of Diabetic Neuropathy by Drs. Grazia Aleppo (the top endocrinologist at Northwestern University) and Gary Jay (a pain specialist in Daytona, Florida). How big a problem is PN? The authors immediately let us know.
“60% to 70% of people with either type 1 or type 2 diabetes will develop some type of diabetic nerve pain over their lifetime, including diabetic peripheral neuropathy (DPN).”
Putting a calculator to this, I estimated that right now, 21 million Americans are dealing with Peripheral Neuropathy. The National Institutes of Health’s Institute of Neurological Disorders and Stroke backed this up, revealing that not only do they estimate 360 million cases worldwide within the next fifteen years, but currently there are…….
“An estimated 20 million people in the United States have some form of peripheral neuropathy, a condition that develops as a result of damage to the peripheral nervous system — the vast communications network that transmits information between the central nervous system. Symptoms can range from numbness or tingling, to pricking sensations (paresthesia), or muscle weakness. Areas of the body may become abnormally sensitive leading to an exaggeratedly intense or distorted experience of touch (allodynia).
In such cases, pain may occur in response to a stimulus that does not normally provoke pain (hyperalgia). Severe symptoms may include burning pain (especially at night), muscle wasting, paralysis, or organ or gland dysfunction. Damage to nerves that supply internal organs may impair digestion, sweating, sexual function, and urination. In the most extreme cases, breathing may become difficult, or organ failure may occur.”
Some of the things the authors blamed Peripheral Neuropathy on included, “GENETICS, INSULIN RESISTANCE, AGES (not to be confused with one’s age), and OXIDATIVE STRESS.” They made it clear that this is another one of those diseases which, if you wait to do something about it until you are actually diagnosed, you are already behind the eight ball. Case in point….
“If presence of symptoms was used as a criterion, 10% to 15% of diabetic patients would have neuropathy. The prevalence increases to 50% when sensory testing and nerve conduction study criteria are included.”
Here’s what’s really crazy about the whole PN thing.Despite the fact that this problem is so common that it could almost be considered an epidemic, these authors tell us that there are only three (3) FDA-approved treatments for it. We learn a little bit about these from January 2015 issue of Therapeutic Advancements in Chronic Disease (Treatment of Painful Diabetic Neuropathy).
“Clinical guidelines recommend pain relief through the use of antidepressants, gabapentin and pregabalin, opioids, and topical agents such as capsaicin. Of these medications, duloxetine [an antidepressant, Cymbalta being the most common] and pregabalin [Lyrica] were approved by the US Food and Drug Administration (FDA) in 2004 and tapentadol [an Opiod]… was approved in 2012.”
What do we know about ANTIDEPRESSANTS in general? Research on this class of drug is so tainted by (PURPOSEFULLY) sitting on or hiding crappy results, that nothing about it can be trusted — nothing. Concerning LYRICA, click the link to read an old article I wrote on this topic. Ask anyone who takes it — the stuff is bad news, with lots of side effects. The link reveals that this is not simply my opinion, but but the opinion of the manufacturers themselves, who admit that it is no better than placebo when it comes to treating, “neuropathic pain symptoms“.
As for Gabapentin; this is the chief drug that Pfizer was fined 2.3 billion dollars for promoting for uses it was never studied for or approved for (HERE). Although this drug works on some level, it works better at higher levels — the same levels that tend to cause the most / worst side effects (SIDE EFFECTS OF GABAPENTIN). And I don’t really even need to mention the problems associated with OPIOIDS, do I? Below are the COCHRANE REVIEW’S findings for amitriptyline (all results cherry-picked — March 2015). Cochrane is considered the best of the best as far as wading through decades of studies and coming to a general conclusion.
“Amitriptyline has been a first-line treatment for neuropathic pain for many years. The fact that there is no supportive unbiased evidence for a beneficial effect is disappointing…. Only a minority of people will achieve satisfactory pain relief. Our best guess is that amitriptyline provides pain relief in about 25% more people than does placebo, and about 25% more people than placebo report having at least one adverse event. The most important message is that… amitriptyline will not work for most people.”
The PPM authors also talked about any number of “natural” substances used to treat Peripheral Neuropathy. Alpha Lipoic Acid is a biggie. So is Vitamin B. The problem with B is that most people using it are NOT USING IT IN ITS NATURAL FORM. They also discussed BOTOX, TENS Units, pain patches, pain sprays, as well as a whole array of “OFF-LABEL” drugs. Suffice it to say, the potential side effects of these drugs (at least the ones that they talked about) were both numerous and severe.
On top of this, we know that said side effects of all drugs are typically under-reported by something like 95% (HERE). The problem with every single one of these approaches is that they leave you trying to play “catch up” after the fact. This is why PREVENTION is the single best gift you can give yourself when it comes to PN; a fact the authors agree with. Pay attention to these next three sentences (particularly the last one) as they could save you a ton of future grief.
“Nerve damage may be present long before diagnosis. Early diagnosis and treatment is paramount to preventing long-term disability. Strict glycemic control remains the only available treatment option to prevent the development of diabetic neuropathy.”
Read that last sentence and let it sink in. There are two ways to maintain strict ‘glycemic control’ (strict regulation of your Blood Sugar). Diet and / or medication. We’ve seen that when it comes to Diabetes, the drugs don’t work any too well — and especially not like they have been touted to work (HERE).
Strangely enough, diet does not always work either. Much of this is due to the fact that Diabetes, contrary to popular belief, is not so much a Blood Sugar problem as it is an Inflammation problem. To control Inflammation, you first have to understand Inflammation (HERE); something that few people take time to do. Secondly, you have to realize that even thought sugar is extremely inflammatory in and of itself (HERE), there are any number of other things that could be driving said Inflammation — despite the fact you strictly control your intake of carbs (HERE).
LOW LEVEL LASER THERAPY FOR TREATING NEUROPATHY

Although there are any number of effective non-pharmacological treatments for Periphreal Neuropathy, the most promising would have to be LLLT (Low Level Laser Therapy). Although I use a COLD LASER in my clinic, I do not do a lot of work treating those with PN. It’s not that I don’t believe in it, it’s simply not the current thrust of my practice. However; not only is there abundant peer-reviewed research on this topic, if you keep the laser moving and don’t shine it in your patient’s eyes, there are no side effects I am aware of. Will it work for you? Who knows?
However, the research on using Laser Therapy to treat PHN (Post Herpetic Neuralgia — the nerve pain from Shingles) would automatically lead me to believe it might (HERE). Let’s look at a few of the studies that lead me to this conclusion.
- In 2004, Diabetes Care (the journal of the ADA) carried a study called Low-Intensity Laser Therapy for Painful Symptoms of Diabetic Sensorimotor Polyneuropathy. The authors concluded that, “Although an encouraging trend was observed with LILT, the study results do not provide sufficient evidence to recommend this treatment for painful symptoms of DSP.” Not exactly a ringing endorsement for LLLT, but skip forward seven years and see what happens as the technology improved.
- The April, 2011 issue of the Journal of Advance Research (Effect of Low Level Laser Therapy on Neurovascular Function of Diabetic Peripheral Neuropathy) came to some interesting conclusions on this subject. “Diabetic neuropathy is the most common complication and greatest source of morbidity and mortality in diabetic patients. Pain intensity via visual analogue scale, bilateral peroneal motor nerves, sural sensory nerves conduction velocity and amplitude and foot skin microcirculation, were measured pre- and post-treatment for both groups. Pain was significantly decreased and electrophysiological parameters and foot skin microcirculation were significantly improved in the laser group, while no significant change was obtained in the control group. Low level laser therapy within the applied parameters and technique could be an effective therapeutic modality in reducing pain and improving neurovascular function in patients with diabetic polyneuropathy.“
- A month later, the May, 2011 issue of Podiatry Today carried an article called Can Low-Level Laser Therapy Have An Impact For Small Fiber Neuropathy?. The four authors did their own study, complete with biopsies, so they could see what is going on at the tissue / cell level. They answer the question posed in the paper’s title by saying that, “These data show a clinically meaningful outcome for the treatment of neuropathic pain without an adverse event.” They described their approach thusly. “An effective therapeutic approach would promote angiogenesis, downregulate inflammation and induce small fiber nerve regeneration. A therapy with such promise is low-level laser therapy (LLLT). Researchers have shown that low-level laser therapy promotes central and peripheral neuron repair; suppression of cyclooxygenase-2 (COX-2); enhancement of peripheral endogenous opioids; upregulation of vascular endothelial growth factor (VEGF); angiogenesis; collagen synthesis and decorin expression during tendon and ligament repair; reduction in fibrosis, suppression of conduction along unmyelinated C fibers; and inhibition of histamine release.” All of these attributes of Low Level Laser Therapy are backed by the peer-reviewed scientific literature on the topic.
- Half a year after this, the September, 2012 issue of the Journal of Comparative Neurology (Low-Level Laser Therapy Alleviates Neuropathic Pain and Promotes Function…..) concluded that, “Low-level laser therapy significantly improved sciatic, tibial, and peroneal functional indices after CCI. The therapy also significantly reduced the overexpressions of HIF-1α, TNF-α, and IL-1β [inflammatory markers], and increased the amounts of VEGF, NGF, and S100 proteins. In conclusion, a low-level laser could modulate HIF-1α activity. Moreover, it may also be used as a novel and clinically applicable therapeutic approach for the improvement of tissue hypoxia / ischemia and inflammation in nerve entrapment neuropathy, as well as for the promotion of nerve regeneration. These findings might lead to a sufficient morphological and functional recovery of the peripheral nerve.“
- A year later (September 2013), the Iranian journal, Acta Medica Iranica carried a study of 60 Diabetics with neuropathy called Evaluation of Low Level Laser Therapy in Reducing Diabetic Polyneuropathy Related Pain and Sensorimotor Disorders. After comparing Laser Therapy to “sham” laser therapy, the authors determined that, “Laser therapy resulted in improved neuropathy outcomes in diabetic patients.“
- If you follow THIS LINK, you’ll quickly see that most problems of the Endocrine System (not just Diabetes) start with BLOOD SUGAR DYSREGULATION. Furthermore, I’ve shown you that FIBROMYALGIA, while typically associated with ADRENAL FATIGUE, is now believed to be a form of all-over SMALL FIBER PERIPHERAL NEUROPATHY. A study published in the May 2013 issue of the Journal of Alternative and Complementary Medicine (Effects of Class IV Laser Therapy on Fibromyalgia Impact and Function in Women with Fibromyalgia) revealed that, “LHT may be a beneficial modality for women with FM in order to improve pain and upper body range of motion, ultimately reducing the impact of FM.“
- Because diabetic foot ulcers are one of the most common sequelae of Diabetic Peripheral Neuropathy, I thought I should include this 2014 meta-analysis from Evidence-Based Complimentary and Alternative Medicine (Low Level Laser Therapy for the Treatment of Diabetic Foot Ulcers: A Critical Survey). After initially looking at almost 2,000 articles on the topic, the authors narrowed the field to 22 studies that met their criteria, concluding that even though, “The transferal of these data into clinical medicine is under debate, cell studies and animal studies gave evidence of cellular migration, viability, and proliferation of fibroblast cells, quicker reepithelization and reformed connective tissue, enhancement of microcirculation, and anti-inflammatory effects by inhibition of prostaglandine, interleukin, and cytokine as well as direct antibacterial effects by induction of reactive oxygen species (ROS). The majority of clinical studies show a potential benefit of LLLT in wound healing of diabetic ulcers. In summary, all studies give enough evidence to continue research on laser therapy for diabetic ulcers.“
- The October, 2015 issue of the medical journal Laser Medicine (Efficacy of Low Level Laser Therapy on Painful Diabetic Peripheral Neuropathy) showed that, “The result analysis showed significant reduction in Pain using VAS scale, reduction in Vibration perception threshold, and a significant increase in the temperature from baseline to post intervention. In the present study, Low level laser therapy was found to be effective in Type II Diabetes Mellitus with peripheral neuropathy.“
- It is important to remember that while Diabetes is the chief reason that people end up with Peripheral Neuropathy, it certainly isn’t the only reason. There are any number of others including CANCER TREATMENT and TREATMENT OF AUTOIMMUNE DISEASES (chemotherapy). Just a few short months ago, the January issue of Supportive Care in Cancer (Low-Level Laser Therapy Alleviates Mechanical and Cold Allodynia Induced by Oxaliplatin Administration in Rats) showed that, “Cold and mechanical allodynia caused by oxaliplatin-induced acute peripheral neuropathy frequently occur after drug infusion. LLLT relieved both cold and mechanical allodynia induced by oxaliplatin in rats. Oxaliplatin-related increases in protein levels of NGF and TRPM8 in DRG and SP in the dorsal horn were also reduced after LLLT. The findings of this study support LLLT as a potential treatment for oxaliplatin-induced neuropathy. Moreover, our findings suggest that SP, TRPM8, and NGF proteins in the superficial dorsal horn and DRG may be involved in an antiallodynic effect for LLLT.” In a nutshell, Laser Therapy helps people with both HYPERALGIA & ALLODYNIA.
*BONUS STUDIES
- There are any number of reasons I am a fan of WHOLE BODY VIBRATION. Add the potential for it to help those with PN to the list. The October, 2013 issue of the Journal of Bodywork and Movement Therapies (Whole Body Vibration Therapy for Painful Diabetic Peripheral Neuropathy: A Pilot Study) published in their abstract that, “The unsatisfactory results associated with conventional treatments for symptoms of diabetic peripheral neuropathy (DPN) demonstrate a need for research into alternative therapies. WBV demonstrated a significant acute pain reduction in the VAS, and a significant chronic reduction in both the VAS and NPS scales. No side-effects were observed during this study. WBV appears to be an effective, non-invasive treatment for pain associated with DPN.“
- Neurosurgeon, Dr. Peter Carney, an expert in Low Level Laser Therapy, is working with a new form of treatment for PN called CET. In a MedScape paper called Peripheral Neuropathy Treatment Taps Into Quantum Theory, Carney reported to the 2014 meeting of the American Academy of Pain Management their amazing results with CET. The treatment involves injecting the problematic nerves with certain kinds of ions and then stimulating them with electricity. He was not only given an award for one of the top studies presented at the meeting, but pushed for further research saying, “If these results are replicated, then millions of people with neuropathy who are in agony may be able to lead fuller lives.“
CONCLUSIONS
Bottom line, if you truly want to help yourself with Peripheral Neuropathy you are going to have to change your diet. Period. Historically, this has meant something along the lines of a LOW CARB or even KETOGENIC DIET (specific info on PN in this link), although I am a huge fan of PALEO. A failure to break your CARB ADDICTION and move away from the HIGH CARB LIFESTYLE is going to doom whatever treatment you use.
The beauty of Low Level Laser Therapy (either Cold, Class III lasers or Class IV lasers that generate heat) is certainly promising in the treatment of Peripheral Neuropathy. Plan on getting treated at least 3 to 4 times a week for a month to see if it is going to help. Unlike the drugs typically used to wage war against PN, properly used lasers have a side effect profile that is just about zero.
As far as the whole getting-rid-of-inflammation thing is concerned, you’ll definitely want to take a look at THIS POST. Remember, if you don’t deal with underlying Inflammation, all other beneficial treatment results will be temporary at best.